

"My blood lipids are normal at every annual check-up—how could I suddenly have a heart attack?"
In cardiovascular wards, this is almost the question asked most often by patients and their families. Many had undergone routine health check-ups before the event, and their reports showed low-density lipoprotein cholesterol (LDL-C), total cholesterol and triglycerides all within the reference range, with nothing apparently wrong. Yet a sudden acute myocardial infarction turns that "normal" lab report into something deeply puzzling.
In fact, this is far from an isolated case. Clinical research in recent years has increasingly shown that conventional lipid markers alone cannot fully reflect a person's true cardiovascular risk.

A prospective study published in 2024, "Outcomes of Patients with Normal LDL-Cholesterol at Admission for Acute Coronary Syndromes: Lower Is Not Always Better," analyzed 1,579 patients experiencing their first acute coronary syndrome who had not previously used statins. The study defined LDL-C <2.6 mmol/L (approximately 100 mg/dL) as the normal range.
The findings produced a striking figure: among these patients suffering a first myocardial infarction, 242 individuals (about 15%) had LDL-C levels that fell entirely within the "normal" range.
This means that for roughlyevery 6 to 7 first-time heart attack patients, 1 had an LDL-C value that looked "normal" on the lab report.

The study also identified a phenomenon worth attention. Compared with patients who had elevated LDL-C, those with normal LDL-C tended to be older and were more likely to have coexisting chronic conditions such as diabetes and chronic kidney disease.
Over a mean follow-up of 43 months, long-term mortality was approximately 27%in the normal LDL-C group, compared with around 14%in the elevated LDL-C group.
This pattern of "better numbers but worse outcomes" is known as the"lipid paradox."It reminds us that a single marker cannot capture cardiovascular risk in full.

Atherosclerosis develops through a complex process that depends on far more than the concentration of cholesterol in the blood. Current research suggests at least three factors may explain this phenomenon.

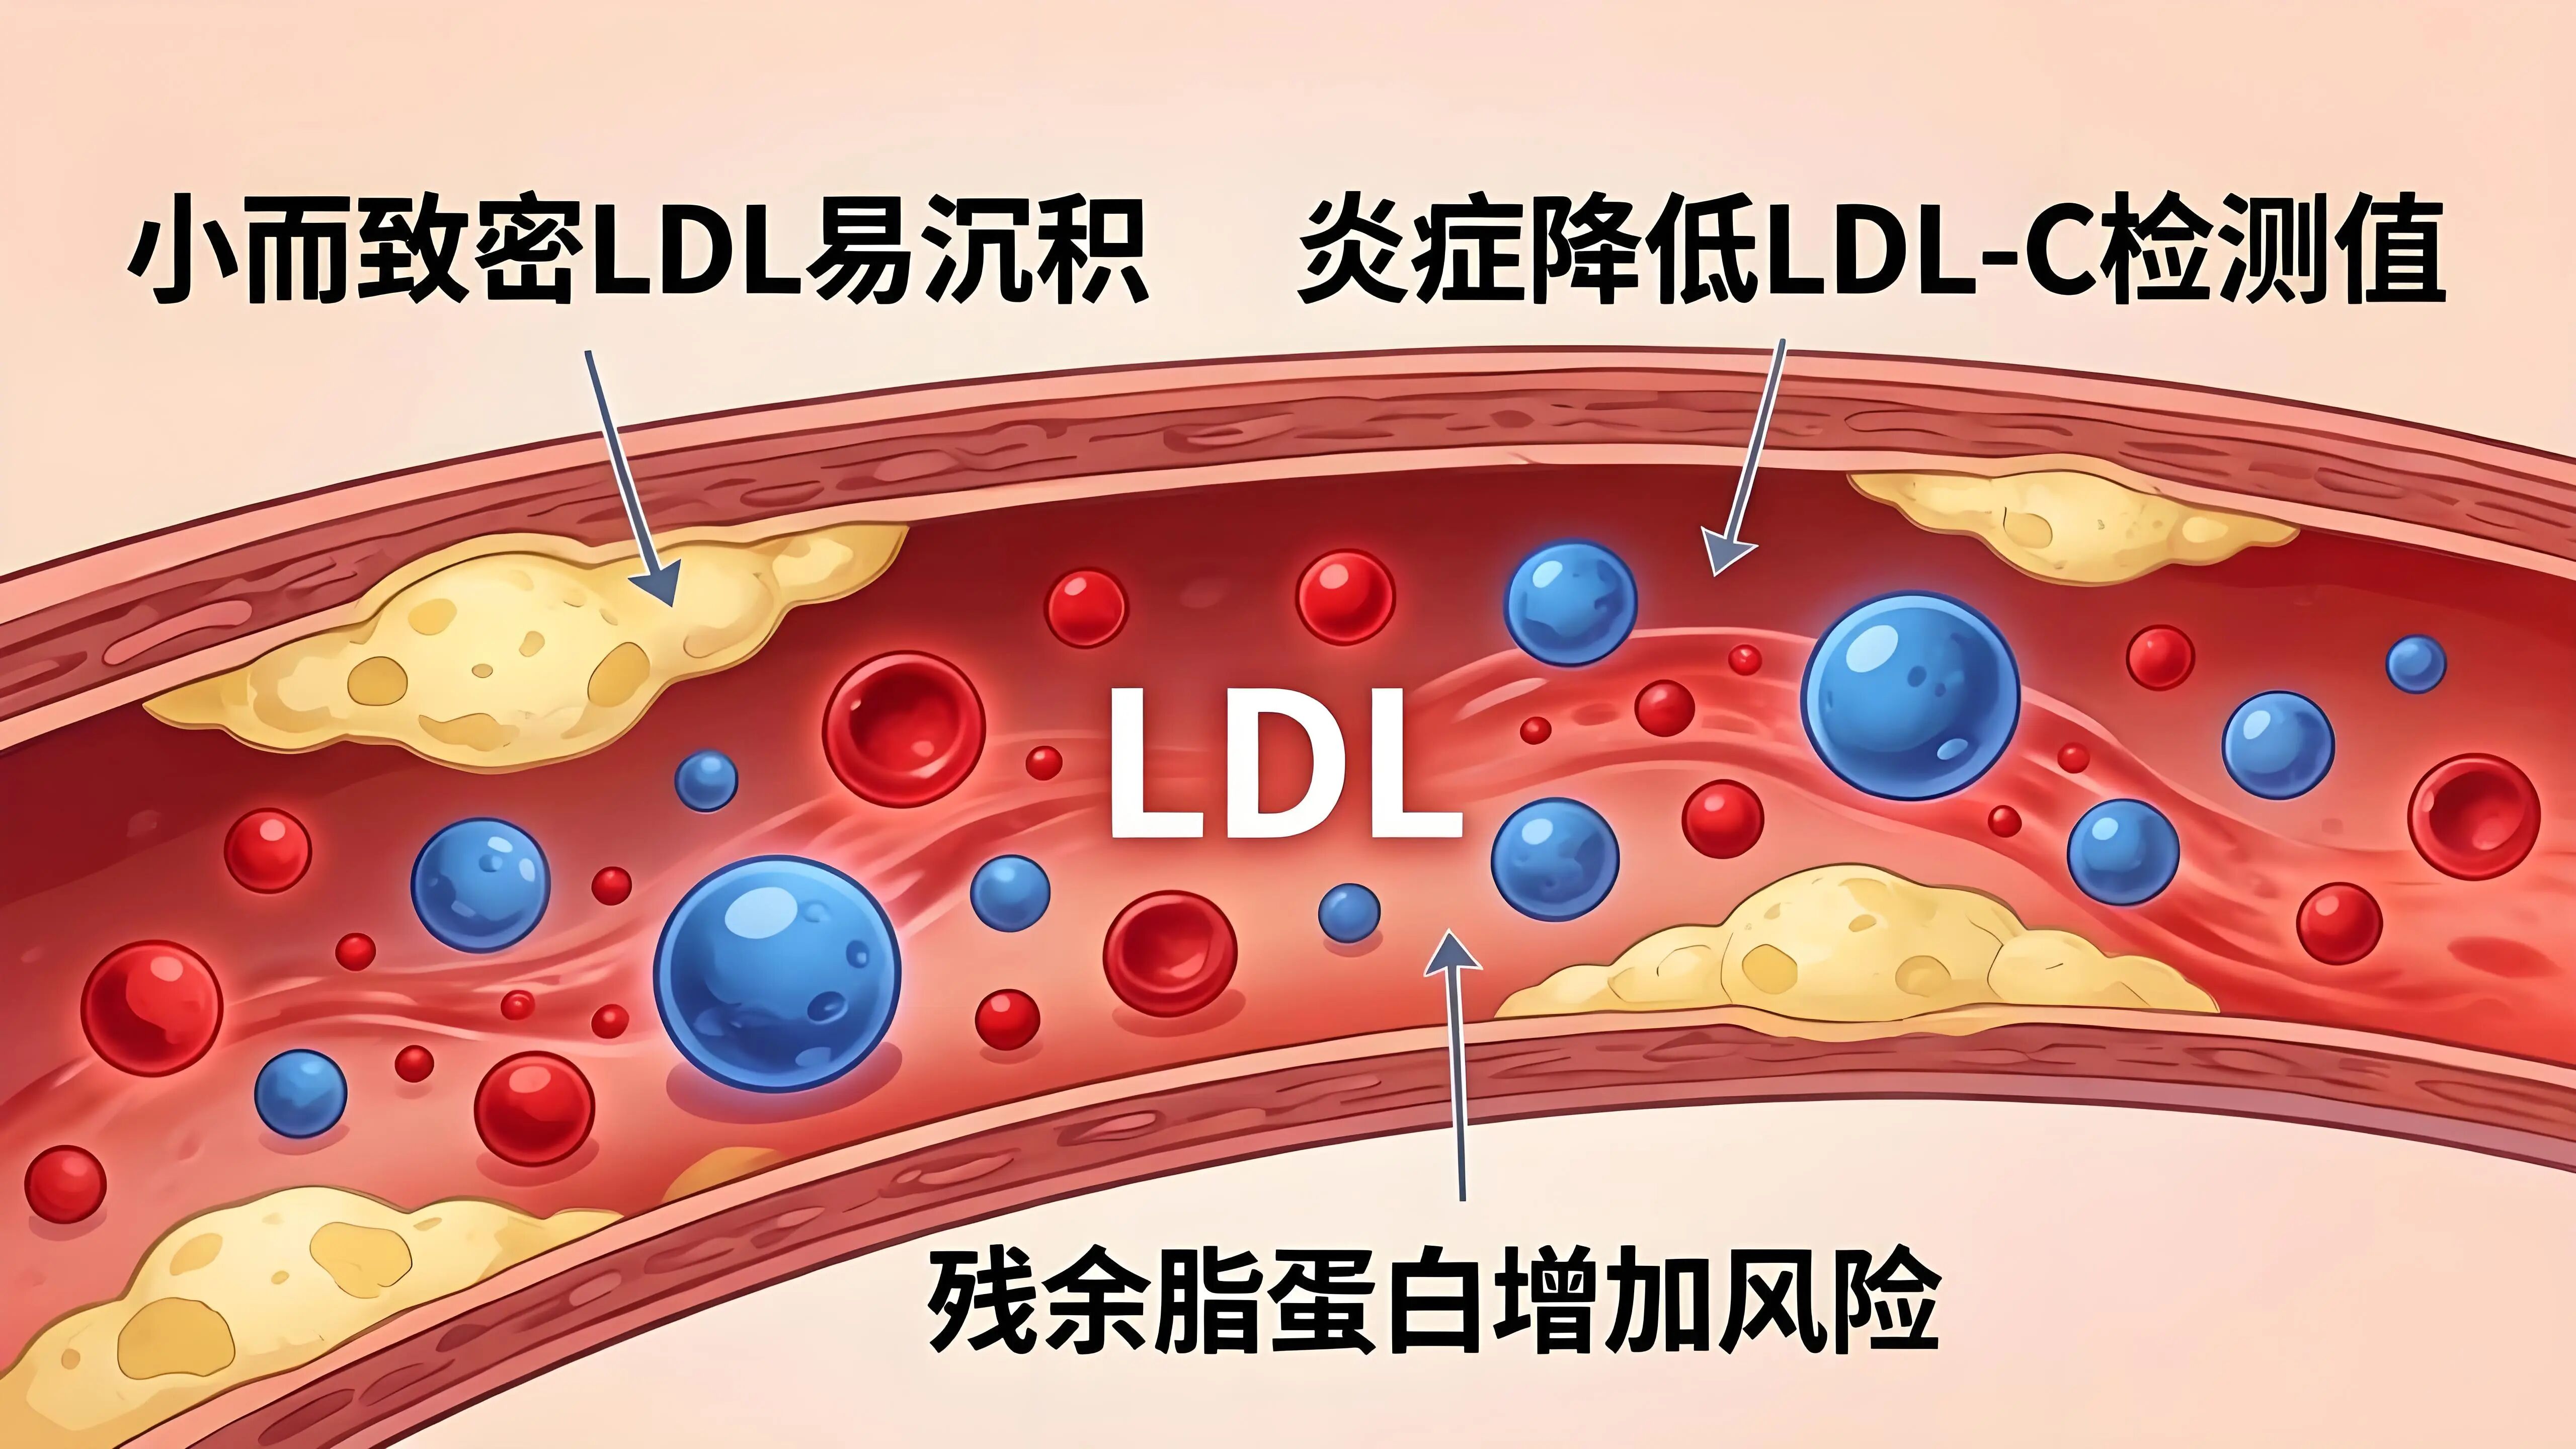
Acute myocardial infarction is itself a powerful inflammatory event. When the body is in a state of severe inflammation, lipid metabolism shifts and LDL-C levels may drop temporarily. A "normal" value measured at admission therefore does not necessarily reflect the patient's usual lipid profile.

Conventional lipid testing reports only the concentration of LDL-C; it says nothing about the structural characteristics of LDL particles. A growing body of research indicates that the number and size of LDL particles, and the distribution of their different subtypes, have a major influence on atherosclerosis risk. Small, dense LDL particles, for example, enter the vascular endothelium more readily and take part in plaque formation, so they may raise the risk of arterial hardening even when total cholesterol content is not markedly elevated.

Conventional lipid panels do not cover several important lipoprotein components, such as triglyceride-rich lipoproteins, very low-density lipoprotein (VLDL), intermediate-density lipoprotein (IDL) and remnant cholesterol. Recent studies show that these lipoproteins also participate in the atherosclerotic process and are closely associated with the risk of cardiovascular events.

Many people judge whether their blood lipids are normal simply by looking for arrows on the lab report: as long as nothing falls outside the reference range, they assume their cardiovascular risk is low. In reality, the "normal range" on a lab report is only a statistical reference for the general population; it is not the same as a personal safety target. Clinical guidelines stress that LDL-C targets should be stratified according to each individual's cardiovascular risk.
For example:
● Extremely high-risk individuals (for example, those with a history of myocardial infarction, stroke or coronary stenting): the LDL-C target generally needs to be kept below 1.4 mmol/L
● Very high-risk individuals: the target is generally 1.8 mmol/Lor lower
In other words, for some high-risk patients, a value that looks "normal" on the lab report may in medical terms already fall within the range that calls for intervention.
So rather than fixating on the arrows on your report, it is more important to ask yourself one question:given my level of risk, is this value really safe?

As research has advanced, the medical community has come to recognize that blood lipids are not simply a handful of numbers, but a complex system made up of many different lipoprotein particles. Conventional testing focuses mainly on cholesterol concentration, whereas more refined methods can further analyze the number of lipoprotein particles and the distribution of their subfractions, enabling a more comprehensive assessment of atherosclerosis risk.
Against this backdrop, comprehensive blood lipid profiling based on nuclear magnetic resonance (NMR) technology is increasingly being applied to finer-grained cardiovascular risk assessment.

LipidVoyage™Comprehensive Blood Lipid Profiling is based on nuclear magnetic resonance (NMR) spectroscopy. From a single blood draw, it provides a more detailed analysis of the lipoprotein particles in the blood. Beyond conventional lipid markers, the assay can also distinguish different lipoprotein particles and their subfractions, helping to build a fuller picture of an individual's lipid profile.
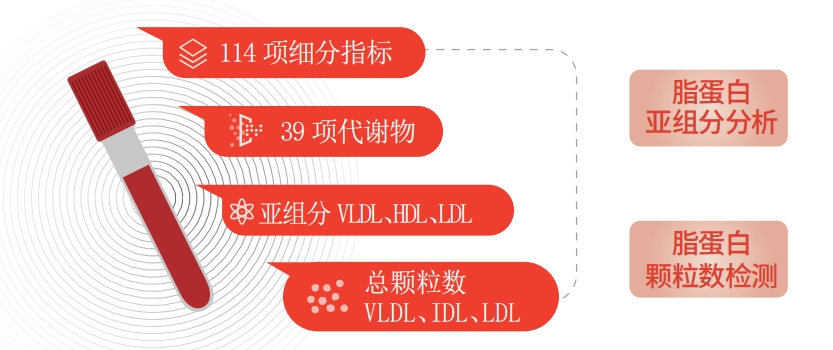
For people whose conventional lipid markers appear normal but who still carry risk factors, this more refined approach can help identify potential risk and provide a reference for subsequent personalized health management.
References:
Jurin I, Jurišić A, Rudež I, et al. Outcomes of Patients with Normal LDL-Cholesterol at Admission for Acute Coronary Syndromes: Lower Is Not Always Better. Journal of Cardiovascular Development and Disease. 2024; 11(4):120.
